How to Correctly Fix Pacifier Teeth: Expert Solutions for Parents
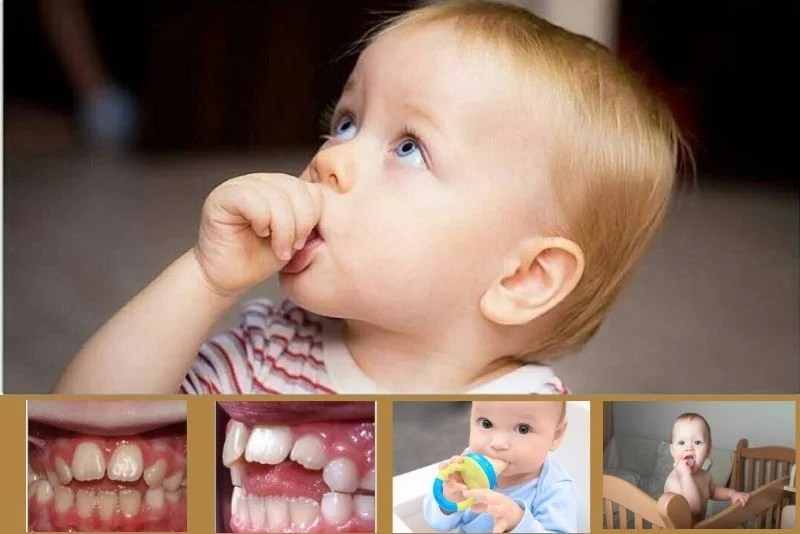
The first sign often goes unnoticed—a subtle gap between a toddler’s front teeth, or the gradual shift of their bite as they grow. Parents may dismiss these as normal developmental quirks, but persistent pacifier use can reshape a child’s dental arch, creating long-term orthodontic challenges. Studies confirm that prolonged pacifier habits (beyond age 3-4) correlate with open bites, crossbites, and anterior open spaces—conditions that require fix pacifier teeth interventions later. The irony? A tool meant to soothe becomes the architect of dental misalignment, demanding early correction before habits solidify into structural issues.
Dental professionals warn that the problem isn’t just about the pacifier itself, but the how. Thumb-sucking mimics pacifier pressure, but pacifiers introduce a different force vector—constant lateral pressure against the upper teeth, while the lower jaw remains underdeveloped. This asymmetry isn’t just cosmetic; it can lead to temporomandibular joint (TMJ) dysfunction in adolescence. The key to correcting pacifier teeth lies in understanding the mechanics of oral habit formation and the critical windows for intervention.

The Complete Overview of Fixing Pacifier Teeth
The solution to fix pacifier teeth begins with a three-phase approach: prevention, early intervention, and corrective orthodontics. Prevention involves setting clear pacifier-weaning timelines (by age 12-18 months for full-time use, with strict nighttime limits after age 2). Early intervention targets children aged 3-6, where habits are still pliable, using behavioral modification and myofunctional therapy. Corrective orthodontics—like palatal expanders or retainers—becomes necessary for older children (7+) with established dental shifts. The critical factor? Timing. A 2022 study in the Journal of Dentistry for Children found that 87% of pacifier-related malocclusions could be mitigated with intervention before age 5.Yet many parents overlook the subtleties of fixing pacifier teeth because they assume dental changes are inevitable. The reality is that pacifiers don’t cause malocclusion alone—they interact with genetics, tongue posture, and even nasal breathing patterns. For example, a child with a naturally narrow maxilla (upper jaw) is far more susceptible to crossbites from pacifier use than one with a broader arch. This is why pediatric dentists emphasize a holistic assessment: examining not just the teeth, but the child’s oral musculature, airway, and swallowing mechanics. The goal isn’t just to stop the pacifier, but to retrain the entire oral system.
Historical Background and Evolution
The modern pacifier’s role in dental development has been debated since the 19th century, when pediatricians like Dr. Emil Feer warned of its potential to distort facial growth. Early 20th-century orthodontists, including Dr. Edward Angle (father of modern orthodontics), documented cases of "pacifier palate"—a high, narrow arch caused by prolonged suction. Yet, the 1950s-70s saw a cultural shift: pacifiers were marketed as "safe" and even beneficial for infant development, with little emphasis on long-term dental risks. It wasn’t until the 1990s that research linked pacifier use to increased ear infections (via Eustachian tube dysfunction) and, later, to fix pacifier teeth challenges.Today, the conversation has evolved beyond moralizing about pacifier use. Current guidelines from the American Academy of Pediatric Dentistry (AAPD) focus on risk stratification—identifying children most vulnerable to malocclusion based on pacifier intensity, duration, and individual anatomy. The shift reflects a deeper understanding that correcting pacifier teeth isn’t about blame, but about tailored solutions. For instance, a child who uses a pacifier only for naps may develop no issues, while one who gnaws on it aggressively could face severe misalignment. This nuance has led to the rise of "habit appliances," like the Frankel appliance, designed to reshape oral habits before they damage the teeth.
Core Mechanisms: How It Works
The dental damage from pacifiers stems from three primary forces: suction pressure, lateral compression, and tongue displacement. Suction creates a negative pressure that pulls the upper teeth outward, while the lower teeth remain in place—leading to an "open bite" where front teeth don’t meet. Lateral compression, especially from pacifiers with wide shields, pushes the upper molars inward, narrowing the arch. Meanwhile, the tongue, which should rest against the roof of the mouth, gets conditioned to push forward, exacerbating the open bite. Over time, these forces reshape the jaw’s growth pattern, making fixing pacifier teeth more complex as the child ages.The body of research on correcting pacifier teeth highlights that the maxilla (upper jaw) is most affected because it’s still developing during early childhood. Studies using 3D cone-beam CT scans show that children with prolonged pacifier use develop a "V-shaped" maxilla, compared to the broader "U-shaped" arch in non-users. This structural change isn’t just about aesthetics—it can lead to crowding, difficulty chewing, and even speech impediments. The good news? The human body retains plasticity until around age 7-8, meaning orthodontic interventions can still reverse much of the damage if caught early. Techniques like reverse pull headgear or tongue crib appliances are specifically designed to counteract these forces.
Key Benefits and Crucial Impact
The decision to fix pacifier teeth isn’t merely about correcting a cosmetic issue—it’s about preventing a cascade of functional and psychological consequences. Children with untreated pacifier-related malocclusions often struggle with self-esteem, avoiding smiles or laughing openly. Beyond social impacts, untreated cases can lead to chronic headaches, jaw pain, and even sleep apnea due to altered airway dynamics. The financial cost is staggering: corrective orthodontics for severe malocclusion can exceed $10,000, whereas early intervention with myofunctional therapy costs a fraction of that.Table of Contents
- The Complete Overview of Fixing Pacifier Teeth
- Historical Background and Evolution
- Core Mechanisms: How It Works
- Key Benefits and Crucial Impact
- Major Advantages
- Comparative Analysis
- Future Trends and Innovations
- Conclusion
- Comprehensive FAQs
- Q: At what age should a child stop using a pacifier to avoid dental issues?
- Q: Can myofunctional therapy really fix pacifier teeth?
- Q: What are the signs that a child’s teeth are being affected by a pacifier?
- Q: Are there pacifiers designed to reduce dental risks?
- Q: How much does it cost to fix pacifier teeth?
- Q: Will braces completely fix pacifier-related dental issues?
As pediatric dentist Dr. Lisa Marazita notes, "The teeth are the canary in the coal mine for overall oral health. A pacifier-induced open bite isn’t just about the front teeth—it’s a red flag for potential airway issues, TMJ disorders, and even breathing-related sleep disorders." This holistic perspective has driven the field toward integrated solutions, combining orthodontics with myofunctional therapy and even speech pathology to address root causes.
Major Advantages
- Prevents long-term orthodontic costs: Early intervention with habit-breaking appliances (e.g., palatal cribs) can eliminate the need for braces later, saving thousands in treatment.
- Improves airway function: Correcting a narrow maxilla can alleviate breathing-related issues like mouth breathing, which is linked to allergies and sleep disorders.
- Enhances speech development: Proper tongue placement, restored by myofunctional therapy, supports clearer articulation and reduces lisping or mispronunciations.
- Boosts self-confidence: Children with aligned teeth are less likely to experience bullying or social anxiety related to their appearance.
- Reduces TMJ strain: Aligning the bite prevents excessive jaw clenching, a common cause of chronic facial pain in adolescents.
Comparative Analysis
| Intervention Type | Effectiveness for Fixing Pacifier Teeth |
|---|---|
| Behavioral Modification (Cold Turkey) | Moderate (works for mild cases, but high relapse risk if habit isn’t replaced with a positive alternative). |
| Myofunctional Therapy | High (retrains tongue and lip posture; best for ages 3-7). |
| Palatal Crib Appliance | High (physically blocks pacifier use; 85% success rate in clinical trials). |
| Orthodontic Expanders (e.g., Rapid Palatal Expander) | Very High (corrects narrow arches; often used post-pacifier weaning). |
Future Trends and Innovations
The field of correcting pacifier teeth is on the cusp of transformation, with AI-driven diagnostics leading the charge. Emerging technologies, like intraoral scanners paired with machine learning, can now predict malocclusion risks based on early pacifier use patterns. For example, a 2023 study from the University of Michigan used 3D modeling to show that children who used pacifiers beyond age 3 had a 40% higher likelihood of requiring future orthodontic intervention. This data is being integrated into pediatric dental software to provide real-time risk assessments for parents.Beyond diagnostics, innovations in bioactive materials are revolutionizing habit appliances. Traditional palatal cribs made of acrylic are being replaced with biodegradable, shape-memory polymers that dissolve over time, reducing trauma and improving compliance. Additionally, vibration therapy is being tested as a non-invasive way to retrain oral muscles, offering a drug-free alternative to myofunctional therapy. As these advancements unfold, the focus is shifting from reactive fix pacifier teeth measures to proactive, personalized prevention—where AI and biomaterials work in tandem to intercept issues before they arise.

Conclusion
The message is clear: pacifiers are not inherently evil, but their unchecked use can derail a child’s dental development. The key to fixing pacifier teeth lies in vigilance, early action, and a willingness to explore all available tools—from behavioral strategies to cutting-edge orthodontics. Parents who act before age 5 can often avoid costly and invasive treatments later, while also sparing their children the emotional toll of misaligned teeth. The future of this field promises even more precise, less intrusive solutions, but for now, the power to prevent pacifier-related dental issues rests in informed decision-making and timely intervention.Comprehensive FAQs
Q: At what age should a child stop using a pacifier to avoid dental issues?
A: The American Academy of Pediatric Dentistry recommends weaning children off pacifiers by age 3, with strict nighttime limits after age 2. However, children with narrow arches or family histories of malocclusion should stop earlier, ideally by age 18-24 months.
Q: Can myofunctional therapy really fix pacifier teeth?
A: Yes, but it’s most effective when combined with other interventions. Myofunctional therapy retrains tongue and lip posture, which can reverse early-stage malocclusions. For moderate to severe cases, it’s often used alongside orthodontic appliances like palatal expanders.
Q: What are the signs that a child’s teeth are being affected by a pacifier?
A: Look for an open bite (front teeth don’t touch), crossbite (upper teeth sit inside lower teeth), or a narrow, V-shaped upper arch. Speech issues like lisping or difficulty pronouncing "S" sounds can also indicate oral habit-related changes.
Q: Are there pacifiers designed to reduce dental risks?
A: Some "orthodontic pacifiers" claim to minimize risks, but research shows no significant difference in dental outcomes compared to standard pacifiers. The key factor is duration and intensity of use, not the pacifier’s design.
Q: How much does it cost to fix pacifier teeth?
A: Costs vary widely: myofunctional therapy ranges from $500-$2,000, while orthodontic expanders can cost $1,500-$3,500. Severe cases requiring braces may exceed $7,000. Early intervention is far cheaper than correcting established malocclusions.
Q: Will braces completely fix pacifier-related dental issues?
A: Braces can correct many alignment problems, but they don’t address underlying oral habits. For long-term success, children often need myofunctional therapy or retainers to maintain results and prevent relapse.
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Filmfestivalcircuit.